
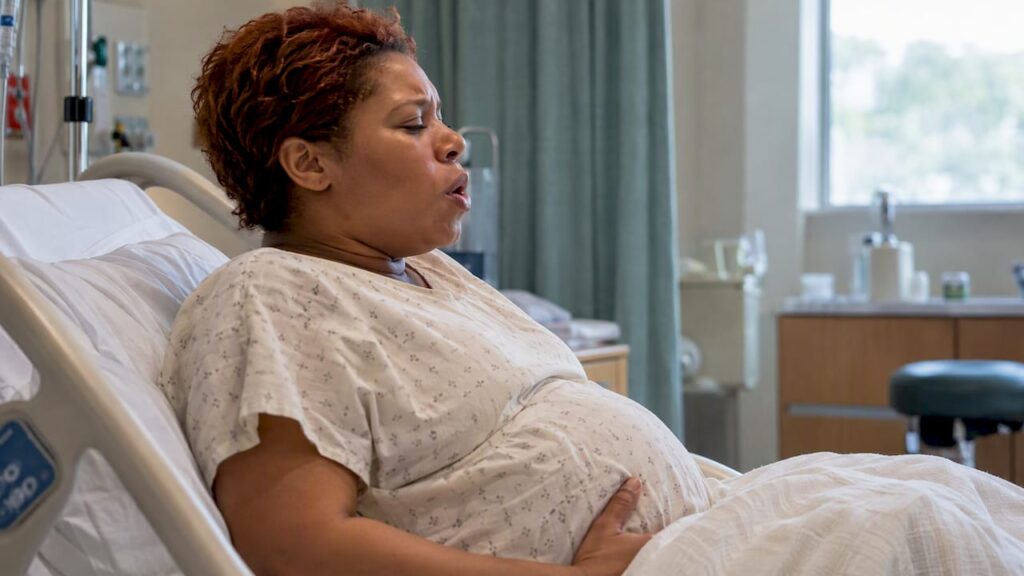
Open glottis pushing means you bear down while breathing out, instead of taking a big breath, holding it and straining for a count of ten. It is often called spontaneous or gentle pushing, because you follow your body’s urge rather than a coach’s count. The research does not crown one method the winner, so the real question is which approach feels right to you and works for your body on the day.
TL;DR
- Open glottis pushing is a long, steady exhale while your abdominal muscles work. Closed glottis (Valsalva) pushing is holding your breath and bearing down.
- ACOG says the evidence does not show one is better, so each person should be encouraged to use her preferred and most effective technique.
- Whether open glottis pushing prevents tearing is still unclear. Trials point in different directions.
- With an epidural, your pushing may be guided more. Ask your provider in advance how they handle that.
- Practice breathing out through effort before labor, so it feels familiar when it counts.
Table of Contents
- What open glottis pushing actually is
- How to push this way, step by step
- What the research says about tearing and your pelvic floor
- Open vs. closed glottis at a glance
- When your team might suggest something different
- How a doula and your partner help at pushing time
- Our perspective: practice the sound, not the technique
- Want to practice before labor?
- FAQ
- Sources
What open glottis pushing actually is
Your glottis is the opening between your vocal cords. When you hold your breath, it closes. When you breathe out, groan or hum, it stays open.
The American Academy of Family Physicians describes open glottis pushing as prolonged exhalation while contracting the abdominal muscles. ACOG notes that when women are not coached to breathe a particular way, they push with an open glottis. It is what many bodies do on their own.
How it differs from spontaneous pushing
The two terms overlap. Spontaneous pushing is about timing and instinct: you push when you feel the urge. Open glottis is about breath: you exhale as you push. Cochrane describes spontaneous pushing as following the woman’s own instincts, usually with three to five pushes per contraction. Directed pushing means a deep breath, held, with bearing down through the whole contraction.

In practice, spontaneous pushing almost always involves an open glottis. Directed pushing usually involves a closed one.
How to push this way, step by step
The American College of Nurse-Midwives describes a simple pattern in its guide to second-stage pushing:
- Wait for the urge to bear down, when your care team agrees it is appropriate.
- Breathe in, then push while you breathe out slowly. Grunting or low, deep sounds are fine.
- Keep each push to roughly five seconds, around three to five pushes per contraction.
- Take a breath between pushes, and rest fully between contractions.
Pro tip: Practice a long “haaa” or a low hum while you tighten your belly during pregnancy. Sound keeps your throat open without you thinking about it.
If your body is not giving you a clear urge, because of an epidural or just a quiet moment, your provider may suggest a different rhythm. That is not failure. It is a tool.
What the research says about tearing and your pelvic floor
This is the part many articles oversell. Here is the honest picture.
Statistic Spotlight: The AAFP’s 2023 review found that three randomized trials showed no overall difference in tears between open and closed glottis pushing. One study of first-time mothers found fewer lacerations and more intact perineums, and tears longer than 2 cm may be less frequent.
So the evidence on perineal trauma is mixed. Other points worth knowing:
- ACOG found no clear differences between spontaneous and Valsalva pushing in second-stage length, spontaneous vaginal birth, episiotomy, perineal lacerations, low five-minute Apgar scores or NICU admission.
- ACOG also notes one trial with more abnormal urodynamic findings at three months postpartum after Valsalva pushing, though the long-term meaning was uncertain.
- The ACNM guide says open glottis pushing may help keep blood flowing to the uterus and baby, reduce exhaustion and lower the chance of tearing, although the pushing stage may run slightly longer.
- The reasoning behind open glottis pushing is that exhaling avoids the high chest pressure of a held breath. Researchers behind the French EOLE trial describe this as a theory under investigation, not a proven clinical outcome.
Cochrane’s review of pushing methods reaches a careful conclusion: the randomized evidence does not reliably show major advantages for either approach. A published evidence review in labor management likewise says both pushing with your own urge and the Valsalva maneuver can be considered.
What that means for you: choose the method that feels workable, and be wary of anyone who promises that a breathing style will guarantee an intact perineum.
Open vs. closed glottis at a glance
| Open glottis (spontaneous) | Closed glottis (directed) | |
|---|---|---|
| Breath | Exhale or sound while pushing | Deep breath, held |
| Timing | Follows your urge | Coached count, often 10 seconds |
| Pushes per contraction | About three to five, around five seconds each | About three |
| Who leads | Your body, with support | Your provider or nurse |
| Evidence | No clear difference in major outcomes | No clear difference in major outcomes |
When your team might suggest something different
Sometimes a care team recommends more direction. ACOG supports starting to push at the beginning of the second stage for first-time mothers with an epidural, noting that delayed pushing has not clearly improved the chance of vaginal birth and carries possible risks such as infection and hemorrhage.
Questions to bring to your provider at a prenatal visit:
- How do you usually guide pushing, and are you comfortable with me following my own urge?
- If I have an epidural, when would you want me to start pushing?
- What would make you recommend directed pushing for me?
- How do you support perineal comfort, such as positioning or warm compresses?
Position matters, too. Our guide to birth positions with an epidural shows how to stay mobile and open even when you can’t feel much. Your hospital room matters as well, and we explain how labor and delivery beds can support different pushing positions.
If birth ends in a cesarean after a long push, recovery is its own chapter. This C-section recovery plan covers the first six weeks. Our own page on postpartum body changes is another gentle place to start.
How a doula and your partner help at pushing time
ACOG states that continuous one-to-one emotional support, from a person such as a doula, is associated with improved labor outcomes. At the pushing stage, that support looks very practical:
- Breathing alongside you, so your exhale stays long and low.
- Reminding you to rest between pushes instead of rushing.
- Helping you into positions that give your pelvis room.
- Giving your partner simple jobs, like cool cloths and steady words.
The ACNM guide says your care provider and support person can encourage trust in your body and support breathing between pushes rather than require breath holding. If your partner wants to feel useful, our partner’s role in childbirth guide is a good read together. For more ways to prepare, see our tips on preparing your mind and body for labor.
Our perspective: practice the sound, not the technique
We have sat with families in Newtown, Doylestown and across Bucks County as they get ready for birth, and we hear the same worry: “Will I know how to push?” Our answer is almost always the same. Your body has more instinct than you think, and what it needs is permission.

We teach open glottis pushing as one comfortable option, never as a rule or a guarantee. The research does not support promising a particular tearing outcome, and we won’t either. What we see help is rehearsal: a long exhale, a low sound, a relaxed jaw and shoulders, repeated in childbirth class until it is familiar. That is also why we encourage you to talk through your preferences with your OB or midwife, including at Trinity Health St. Mary, well before labor.
If your pushing ends up directed, with a count and a held breath, you have not done it wrong. You still get to feel informed, included and heard.
— Alexis Wallace
Want to practice before labor?
Pushing is far easier to trust when you have rehearsed it with someone who knows your preferences. In our childbirth education classes, we walk through breathing, positions and questions for your provider, tailored to your family. During labor itself, our birth doula support means one steady person stays with you through every stage, including pushing.
FAQ
Is open glottis pushing better than holding your breath?
Not according to the best available evidence. ACOG and Cochrane both say research has not shown clear, major advantages for either method. Many people find exhaling more comfortable, so it is reasonable to start there.
Does open glottis pushing prevent tearing?
It might help some people, but it is not proven. The AAFP review found no overall difference in tears across three trials, with one study of first-time mothers showing fewer lacerations. Ask your provider about positioning and other comfort measures for the perineum.
Can I push this way with an epidural?
Often yes, but your team may guide you more because you feel less urge. Ask your provider ahead of time how pushing is handled with an epidural, and when they would want you to begin.
How do I get ready to push naturally?
Practice exhaling with a low sound while engaging your belly, and learn a few labor positions. A childbirth class or doula can rehearse this with you. Our free consultation is a gentle way to start, and we would be glad to talk through your birth preferences whenever you are ready.
Sources
- ACOG: Approaches to Limit Intervention During Labor and Birth
- Cochrane: Pushing methods for the second stage of labour
- AAFP: Open Glottis During Delivery and Perineal Trauma
- ACNM: Second Stage of Labor: Pushing Your Baby Out
- EOLE trial protocol on maternal pushing type
- Evidence-based labor management: second stage of labor
- C-section recovery plan, weeks 1 to 6