
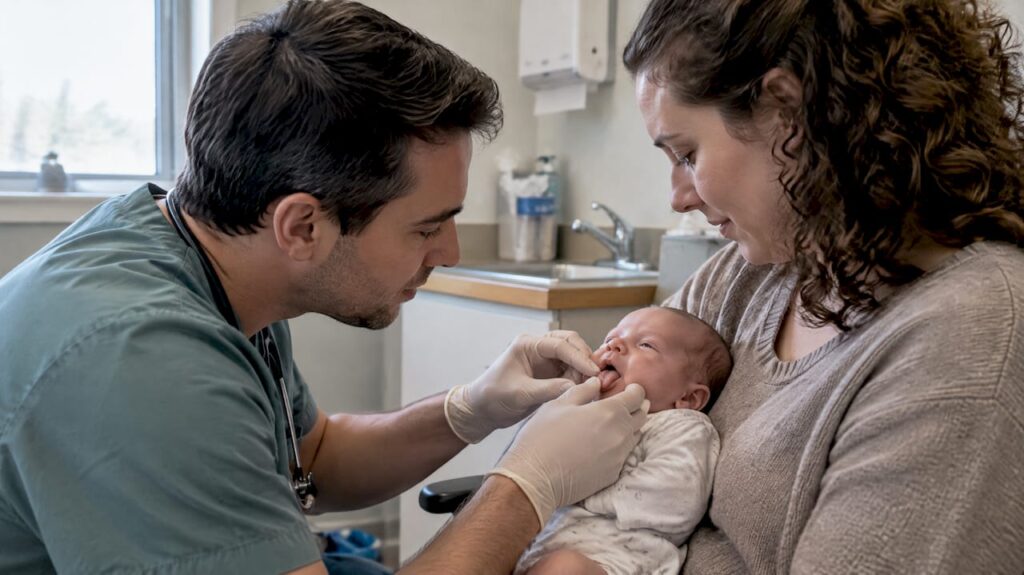
If nursing hurts, your baby slips off the breast, or someone has just mentioned “tongue tie,” you are probably tired and wondering whether something is wrong. The most common signs are a shallow latch, clicking sounds while feeding, nipple pain, and a tongue that looks heart-shaped or can’t lift or stick out far. But those signs have many possible causes, and a tight band under the tongue is only one of them. Here is how to tell what you are seeing, and what to ask before anyone reaches for scissors.
TL;DR
- Tongue tie (ankyloglossia) is a short or tight band of tissue under the tongue. It is estimated to affect 4% to 10% of newborns, and fewer than half of those babies have trouble nursing.
- Common signs: a hard time latching deeply, painful feeds for you, and a tongue that can’t lift or extend well.
- Lip tie is a similar band under the upper lip. Looking at it alone doesn’t tell you whether feeding is affected.
- Look at feeding first: diapers, weight, and how you feel. Ask your pediatrician about a full feeding assessment before any procedure.
Table of Contents
- What tongue tie actually is
- Tongue tie symptoms: what you may notice
- Lip tie vs. tongue tie
- Symptoms that are not necessarily tongue tie
- When to call your pediatrician right away
- What the evidence says about treatment
- Questions to bring to your pediatrician
- Our perspective as a Bucks County doula
- Support that goes beyond the latch
- FAQ
- Ready for calm, personal support?
- Sources
What tongue tie actually is
The American Academy of Pediatrics (AAP) describes ankyloglossia as a condition present at birth in which a short or tight band of tissue, the lingual frenulum, tethers the tip of the tongue to the floor of the mouth. The AAP also treats it as a normal anatomical variation. That means seeing a frenulum doesn’t equal having a problem.
The real question is function. Can your baby move the tongue well enough to feed comfortably and gain weight?
Tongue tie symptoms: what you may notice
You don’t need a medical degree to observe your baby. These are the things worth jotting down.
In your baby
- A tongue tip that looks notched or heart-shaped when your baby cries or lifts it
- Difficulty lifting the tongue toward the roof of the mouth or moving it side to side
- A tongue that can’t reach past the lower gum or lip
- Slipping off the breast, a shallow latch, or a clicking sound while feeding
- Long, frustrating feeds, or falling asleep at the breast without seeming full
In you
The AAP notes that maternal pain is one of the most common complaints, because a tongue that can’t extend and lift may compress the nipple. You might notice:
- Pinched, creased, or blanched nipples after a feed
- Cracked or damaged skin that doesn’t heal
- Pain that continues past the early days even with a position change
Pro Tip: Take a 30-second phone video of a feed and of your baby crying with the tongue lifted. It helps you describe what you see to your pediatrician or lactation consultant.
Lip tie vs. tongue tie
They are cousins, not twins.
| Tongue tie | Lip tie | |
|---|---|---|
| Where | Band under the tongue | Band connecting the upper lip to the gum |
| What it may limit | Tongue lift and extension | How far the upper lip flares out |
| What matters most | Whether feeding is affected | Whether feeding is affected |
Both are about anatomy. Neither is a diagnosis on its own. We always bring parents back to how feeding is going, not how the mouth looks.
Symptoms that are not necessarily tongue tie
The internet lists everything from reflux to mouth breathing as a sign. Be gentle with yourself here. Latch trouble and nipple pain have many causes besides tongue tie, including positioning, milk supply, and a baby’s own tone and sleepiness. AAP experts have also voiced concern that rising diagnoses may be driven by social media trends and outside pressure more than clinical need.
Statistic Spotlight: In one study of 115 infants referred for surgery, 63% did not need the procedure to resolve their feeding issues.

When to call your pediatrician right away
Some signs are about intake, not tongues. The AAP’s guidance is that by day 5 a baby should have at least 3 stools daily, along with 4 to 6 wet diapers a day and a return to birth weight. Call your pediatrician if you see:
- Fewer wet or dirty diapers than expected
- Yellowing of the skin that persists or spreads
- A baby who is hard to wake or consistently very fussy at feeds
- Weight that isn’t coming back up
The CDC says to see your baby’s doctor the same day if your baby is very yellow, hard to wake, or not feeding well. Don’t wait for a tongue tie conversation.
What the evidence says about treatment
A frenotomy is a quick snip of the frenulum. Here is what the research and the AAP say:
- The Cochrane review of frenotomy is the main place to read the trial evidence yourself.
- It can offer a short-term reduction in maternal nipple pain, but there is no consistent evidence of long-term breastfeeding gains.
- The AAP suggests reserving surgery for significant functional impairment, after skilled lactation support has been tried.
- There is no evidence favoring lasers over scissors, and the AAP advises against post-procedure stretching exercises, which are painful and unproven.
- Early frenotomy has not been shown to prevent later speech, dental, or sleep problems. Those have many causes, and speech concerns are often handled with speech therapy.
“Wait and see” is also a legitimate plan. The band can stretch and lengthen with feeding and growth.
Questions to bring to your pediatrician
We don’t diagnose, and we won’t tell you what to do medically. We can help you walk into the appointment prepared. Consider asking:
- Has someone watched a full feed, not just looked under the tongue?
- Could positioning, supply, or another factor explain what we’re seeing?
- Is my baby gaining weight as expected?
- Would a lactation consultant, speech-language pathologist, or second opinion help first?
- If a procedure is recommended, who performs it, and how will we know it helped?
If a procedure is on the table, some families like to see how other pediatric clinics structure a pre-procedure consultation for children, so they know a thorough, coordinated assessment is a reasonable thing to expect.
Our perspective as a Bucks County doula

In more than ten years of supporting families around Newtown, Doylestown, and Trinity Health St. Mary, we’ve seen how quickly a worried whisper about “a tie” can become the only story. A mom in pain at 3 a.m. wants a fix, and that is completely human.
What we do is slow things down. We watch a feed with you, check positioning, and look at the whole picture: your recovery, your baby’s cues, and your confidence. Often the shift is as simple as a new hold or feeding earlier, before crying starts. If it isn’t, we help you take clear notes to your provider, because the decision belongs to you and your care team. Tired parents deserve to feel held between appointments, not rushed.
— Alexis Wallace
Support that goes beyond the latch
Our postpartum care brings calm, hands-on help into your home or onto a video call, and our home breastfeeding visits give you time to ask every question. If you’re still pregnant, childbirth education helps you know what to expect from feeding before the baby arrives.
FAQ
How do I know if a tongue tie is a problem?
It’s a problem when it limits function: painful or ineffective feeding, poor weight gain, or a baby who can’t stay latched, despite skilled help. How it looks isn’t enough. Ask your pediatrician for a full feeding assessment.
Do babies outgrow tongue ties?
Sometimes. The band can stretch and lengthen with feeding and growth, and the AAP-linked guidance treats watchful waiting as a valid approach. Your pediatrician can tell you whether that fits your baby.
Does a tongue tie need to be corrected?
Not always. The AAP suggests considering a procedure only when there is significant functional impairment that hasn’t improved with expert lactation support. Ask about a second opinion if you feel pushed.
Is lip tie the same as tongue tie?
No. Lip tie involves the band under the upper lip, tongue tie the band under the tongue. In both, the question that matters is whether feeding is affected.
Ready for calm, personal support?
If you’d like someone in your corner before or after your baby arrives, we’d love to meet you. Book a free consultation and tell us what’s on your mind.
Sources
- Tongue Tie in Babies: How Ankyloglossia Affects Breastfeeding, HealthyChildren.org
- AAP Addresses Rise in Tongue-Tie Diagnoses, HealthyChildren.org
- Jaundiced Newborn symptom checker, HealthyChildren.org
- Jaundice and Kernicterus Information for Families, CDC
- Frenotomy for tongue-tie in newborn infants, Cochrane via PubMed
- Identification and Management of Ankyloglossia, AAP Clinical Report
- HealthyChildren.org