
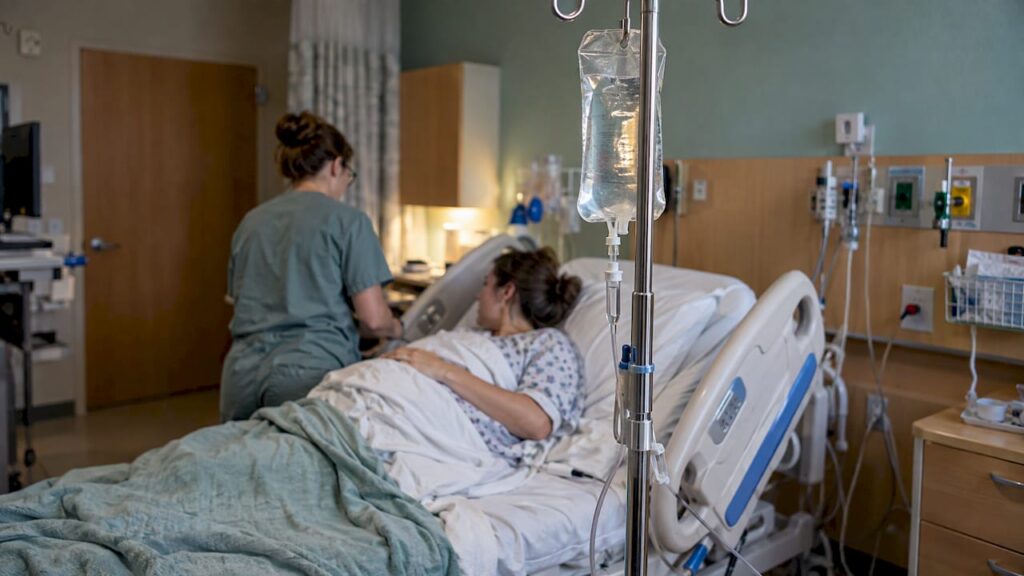
IV fluids in labor are salt-and-sugar solutions given through a thin tube in a vein, usually in your forearm. They are common, and they are often a choice you can talk through ahead of time. The most useful thing you can do is learn the options now, then ask your provider which ones fit your labor. Here is what the research says, in plain words.
TL;DR
- An IV line (the tube in your vein) and IV fluids (what runs through it) are two different things. You can have the line without a continuous drip.
- Many hospitals give IV fluids routinely, and they are often used before an epidural. ACOG notes that women in spontaneously progressing labor may not need a routine continuous infusion.
- Research on fluid volume and labor length is mixed, and amounts matter for your baby’s early weight loss and breastfeeding.
- Common options include a saline lock, drinking clear fluids, or a set fluid rate. Ask your provider which apply to you.
- Put your preferences in writing and talk them through at a prenatal visit, not mid-contraction.
Table of Contents
- IV line versus IV fluids: the difference that matters
- What is actually in the bag
- Why hospitals use them
- What the research says
- Can you drink instead?
- What changed recently
- Can you decline IV fluids?
- How we approach it
- Preparing with personal support
- FAQ
- Sources
IV line versus IV fluids: the difference that matters
An IV line is a thin plastic tube placed in a vein. It can be used to give medicine, and fluids are usually started once active labor begins or when you have an epidural.
A saline lock (sometimes called a heparin lock) is a middle path. The tube sits in your vein, capped off and not attached to a bag. Some hospital worksheets describe it as giving immediate vein access in an emergency while you stay free to move.
That is why “Do I have to get an IV?” is really two questions: do you want the line, and do you want fluids running through it?
What is actually in the bag
The three solutions most used in US labor rooms are normal saline, Ringer’s lactate, and dextrose solutions. Evidence Based Birth explains that saline and Ringer’s lactate are isotonic, meaning they match your body’s own fluid balance. Dextrose adds sugar for calories.

If you have heard worry that sugar in the bag could lower a baby’s blood sugar, ACOG’s review says recent randomized trials did not find increased newborn low blood sugar after continuous 5% dextrose in saline. A good question for your provider: which solution does your hospital typically use, and why?
Why hospitals use them
Three reasons come up most often.
- Hydration and energy. Labor is work, and you may not feel like drinking.
- Epidural preparation. Epidurals can lower blood pressure, so an infusion is typically given beforehand. Your anesthesiologist can talk through the risks, benefits and alternatives.
- Ready access. Medicines or fluids can start quickly if something changes.
The practice is widespread. The most recent national survey Evidence Based Birth cites found that 62% of people received continuous IV fluids in labor. A later California hospital survey found 76% with a midwife attendant and 87% with an obstetrician.
If you are curious how an epidural fits into your labor, our guides on whether an epidural speeds up labor and birth positions with an epidural are good next reads.
What the research says
Statistic Spotlight: A 2017 meta-analysis of 1,215 people found that fluids at 125 mL per hour, compared with 250 mL per hour, were linked to labors about an hour longer and a 30% higher cesarean risk, according to Evidence Based Birth’s handout.
That finding does not settle the question. A 2012 randomized trial of 293 people found no differences in labor length, cesareans or complications between oral fluids alone and oral plus IV fluids at either rate. It did find less vomiting with more IV fluid: 6% at 250 mL per hour, 11% at 125 mL, and 24% with oral fluids only.
Other findings worth knowing:
- Labor length. Of the few trials comparing IV fluids with none among people free to drink, two combined showed IV plus oral fluids shortening labor by about 30 minutes, and the authors did not consider that enough to justify routine use. A third trial with dextrose reported a much bigger difference.
- Your newborn. Babies of people who received more than 2,500 mL of IV fluid were more likely to lose weight after birth, per the same handout. Higher volumes were also tied, in a small study, to more breast tenderness and firmness afterward. If you plan to breastfeed, it is fair to ask how much fluid you will likely receive.
- Fluid overload. Too much IV fluid can collect in the lungs and other tissues. Evidence Based Birth notes this is less likely in young people with healthy hearts and kidneys, and no cases appeared in the trial above.
The honest summary is that the research is evolving, and your own health history matters most. That is a conversation for your obstetrician or midwife.
Can you drink instead?
In many cases, asking is reasonable. A 2017 summary of ACOG’s recommendations advises clear liquids in labor and notes that evidence does not support restricting oral fluids and that IV lines can limit movement.
Hospital rules still vary. Some worksheets note that fluids may be limited to ice chips during induction or augmentation, or when an epidural is planned. So ask early whether your hospital allows clear fluids and what counts as clear. Our guides to eating and drinking in labor and our Laborade recipe cover what many families prepare.
What changed recently
A 2024 nationwide IV fluid shortage pushed obstetric teams to rethink routines. Guidance published in AJOG MFM in November 2024 recommends avoiding unnecessary continuous infusions and stopping fluid boluses before neuraxial anesthesia where possible. It also says people with conditions such as sepsis, postpartum hemorrhage or unstable circulation should not have fluids reduced.
That last point is a reminder that IV access and fluids are sometimes essential. Your care team decides based on your situation.
Can you decline IV fluids?
You have a right to be informed and to ask questions. Many hospitals’ own forms reflect this. Cleveland Clinic’s worksheet lets you keep an IV in place but drink clear fluids rather than have an infusion. Mount Sinai’s birth plan offers a capped-off IV with fluids by mouth. ACOG’s sample birth plan offers an IV line, a saline lock, or no preference, and reminds you that a plan does not guarantee how labor will go.
Questions to bring to your next prenatal visit, whether you deliver at Trinity Health St. Mary or another hospital near Newtown or Doylestown:
- Is a continuous IV routine here, or is a saline lock an option?
- If I have an epidural, what fluids will I receive beforehand, and how much?
- Can I drink clear fluids in early and active labor?
- Given my health history, is there a reason I should have fluids running?
- If I’m induced, what will the fluid policy be?
Our guide on induction methods can help you prepare for that last one.
How we approach it
Over the years I’ve sat with many families who felt blindsided by the IV, not because it was wrong, but because nobody had told them it was a choice to discuss. We believe an empowered birth starts with being informed, not with having every preference granted.
In our work, we help you turn questions like the ones above into a short, calm conversation with your provider, whether you hope for a natural, medicated or cesarean birth. We hold the plan with you between appointments, so you are not carrying it alone.
Alexis Wallace
Preparing with personal support
If you would like someone beside you who knows your preferences and can help you ask good questions, our Pregnancy & Birth Doula service offers personalized, evidence-based, nonjudgmental support before, during and after birth. Our childbirth education classes are also a good place to work through hospital routines like IVs, with your partner alongside you.
We serve families across Bucks, Montgomery, Philadelphia and Burlington Counties, including Newtown, Doylestown and the Princeton area.
FAQ
Do I have to get an IV in labor?
Not always in the same way. The line and the fluids are separate decisions, and options such as a saline lock exist. Your health history and hospital policy shape what is possible, so raise it at a prenatal visit.
Does an epidural require IV fluids?
Hospitals commonly give fluids before an epidural to help keep blood pressure steady. Newer guidance encourages avoiding unnecessary boluses. Ask your anesthesiologist what they plan and why.
Can IV fluids affect breastfeeding?
Research links larger IV volumes, over 2,500 mL, with more early newborn weight loss. Ask your provider how much fluid is typical, and share your feeding plans with your care team.
Can a doula help me talk about IV fluids with my provider?
Yes. A doula can help you prepare your questions and keep your preferences front of mind during labor. If you’d like to talk it through, we’d love to set up a free consultation.
Sources
- Labor | Johns Hopkins Medicine
- Evidence on: IV Fluids during Labor | Evidence Based Birth
- IV Fluids during Labor handout | Evidence Based Birth
- Approaches to Limit Intervention During Labor and Birth | ACOG
- Approaches to Limit Intervention During Labor and Birth (full text)
- Labor preferences worksheet | Women’s Health
- New Professional Recommendations to Limit Labor and Birth Interventions | National Partnership
- Evidence-based obstetric guidance in the setting of an IV fluid shortage | AJOG MFM
- Birth Preferences Worksheet | Cleveland Clinic
- Birth Plan | Mount Sinai
- Sample Birth Plan | ACOG